Diabetic macular edema tests and diagnosis may sound like the sort of phrase that belongs on a clipboard in a very quiet medical office. But if you have diabetes, blurry central vision, wavy lines, trouble reading, or a suspiciously unhelpful pair of glasses, understanding these tests can make a real difference. Diabetic macular edema, often shortened to DME, happens when damaged retinal blood vessels leak fluid into the macula, the small central area of the retina responsible for sharp, detailed vision. Think reading, driving, recognizing faces, checking your phone, and judging whether that “8” is actually a “3.”
The tricky part is that DME can sneak in quietly. Some people notice blurred or distorted vision. Others have no symptoms at first and only learn something is wrong during a diabetic eye exam. That is why eye doctors do not rely on guesswork, vibes, or “I can still see pretty well.” They use a combination of clinical examination and advanced imaging to find swelling, measure retinal thickness, identify leaking vessels, and decide whether treatment is needed.
This guide explains the major tests used to diagnose diabetic macular edema, what each test shows, what patients can expect, and why early detection is one of the best ways to protect vision.
What Is Diabetic Macular Edema?
Diabetic macular edema is a complication of diabetic retinopathy, the eye disease caused by long-term damage to small blood vessels in the retina. When diabetes affects these tiny vessels, they may weaken, bulge, leak, or close off. If fluid leaks into or near the macula, the retina can swell. Because the macula handles central vision, even a small amount of swelling in the wrong place can cause noticeable vision changes.
DME may affect one eye or both eyes. It can occur in people with type 1 diabetes, type 2 diabetes, or diabetes during pregnancy. The risk generally increases with longer duration of diabetes, high blood sugar, high blood pressure, kidney disease, high cholesterol, smoking, and more advanced diabetic retinopathy.
Common Symptoms That May Lead to Testing
Some people are tested for DME because their routine diabetic eye exam shows suspicious changes. Others schedule an appointment because something about their vision feels off. Common warning signs include:
- Blurred or hazy central vision
- Wavy, bent, or distorted lines
- Difficulty reading small print
- Colors looking faded or washed out
- Dark or empty spots near the center of vision
- Vision that changes from day to day
- Trouble recognizing faces or seeing details
These symptoms do not automatically mean diabetic macular edema. Other eye conditions can cause similar problems. Still, if you have diabetes and your central vision changes, that is not a “wait until next year” situation. It is a “call the eye doctor and do not let your calendar bully your retina” situation.
Who Diagnoses Diabetic Macular Edema?
DME is usually diagnosed by an ophthalmologist, often a retina specialist. Optometrists also play an important role in diabetic eye screening and may detect signs that require referral. In many cases, your diabetes care team, primary care clinician, endocrinologist, and eye doctor work together because eye health is closely tied to blood sugar, blood pressure, cholesterol, and overall vascular health.
A regular vision test for glasses is not enough. A diabetic eye exam looks deeper, literally. It checks the retina, blood vessels, optic nerve, macula, and signs of diabetic retinopathy. The macula is small, but it is a very demanding little piece of equipment.
The Main Tests Used to Diagnose Diabetic Macular Edema
1. Comprehensive Dilated Eye Exam
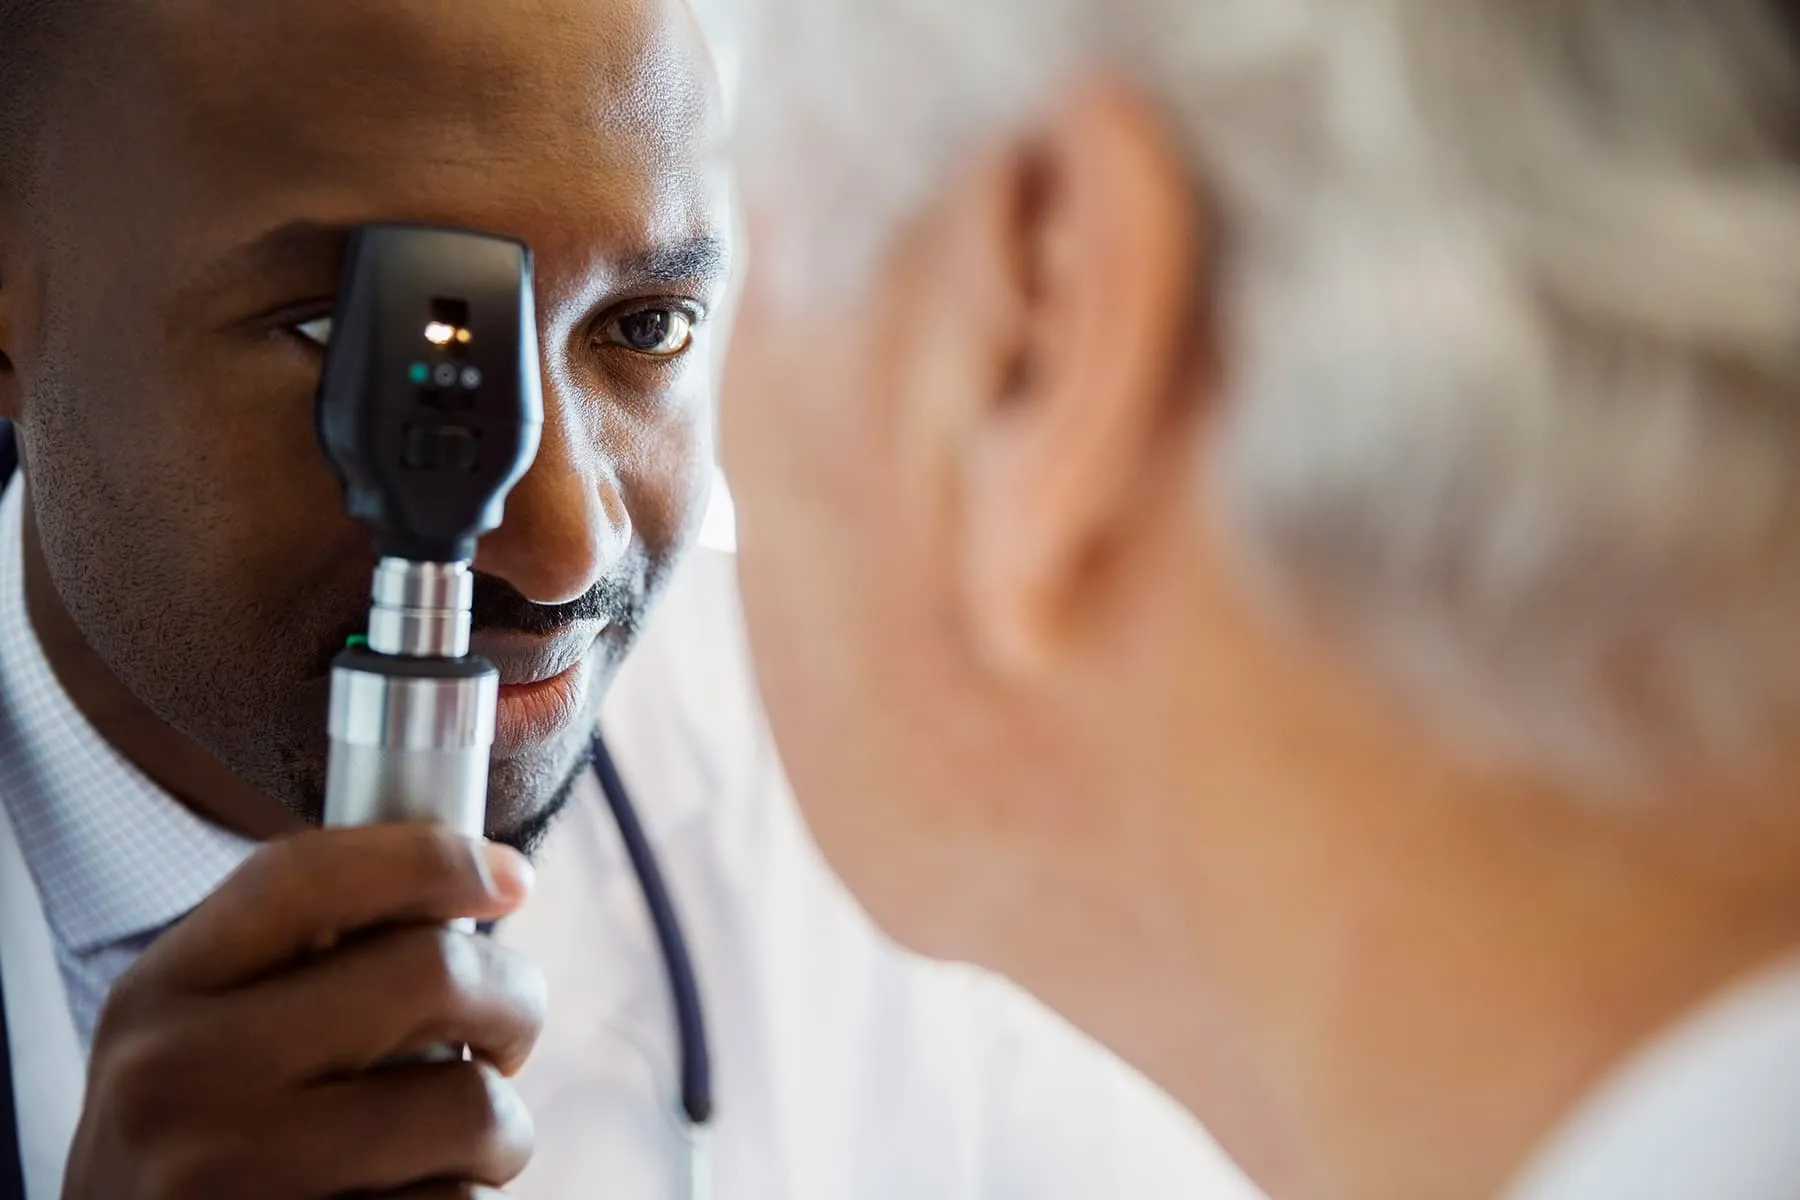
The comprehensive dilated eye exam is the foundation of diabetic eye care. During this exam, eye drops are placed in the eyes to widen the pupils. Once the pupils are dilated, the doctor can examine the retina more clearly using special lenses and lights.
During the retinal exam, the doctor looks for signs such as microaneurysms, bleeding, hard exudates, cotton wool spots, abnormal blood vessels, and retinal thickening. In DME, the doctor may see swelling or yellowish deposits near the macula, which suggest leakage from damaged blood vessels.
Dilation can make vision blurry and increase light sensitivity for several hours. Sunglasses are helpful afterward, unless your goal is to walk outside looking like a startled raccoon. Many patients prefer to have someone drive them home, especially if they are sensitive to bright light.
2. Visual Acuity Test
The visual acuity test is the familiar eye chart exam. You read letters from a distance, usually with one eye covered at a time. This test measures how clearly you can see, but it does not show why vision is reduced. Someone with DME may still read fairly well early on, especially if swelling has not affected the very center of the macula.
Visual acuity is important because it gives the doctor a baseline. If treatment begins, future eye chart results can show whether vision is improving, stable, or worsening. However, a normal eye chart result does not rule out early diabetic macular edema. That is why imaging tests are so valuable.
3. Optical Coherence Tomography (OCT)
Optical coherence tomography, or OCT, is one of the most important tests for diabetic macular edema. It is quick, painless, noninvasive, and extremely useful. OCT uses light waves to create detailed cross-sectional images of the retina. If the retina were a layered cake, OCT would show the slices. Thankfully, no cake or retina is harmed.
OCT can show:
- Retinal thickening
- Fluid-filled cyst-like spaces within the retina
- Fluid under the retina
- Changes in retinal layers
- Whether swelling involves the center of the macula
- How the retina responds to treatment over time
OCT is especially helpful for identifying center-involved diabetic macular edema, which means the swelling affects the central macula. This distinction matters because center-involved DME is more likely to threaten detailed vision and may influence treatment decisions.
During the test, you place your chin on a rest and look at a target while the machine scans the back of the eye. There is no needle, no dye, and no dramatic medical soundtrack. The scan usually takes only minutes.
4. Fundus Photography
Fundus photography takes detailed pictures of the retina. These images help document diabetic retinopathy and may show hemorrhages, exudates, swelling, and other visible changes. Fundus photos are commonly used for screening, monitoring, and comparison over time.
Photographs are useful because they create a record. If your retina changes six months later, the doctor can compare current images with older ones instead of relying on memory. Even excellent eye doctors should not have to play “spot the difference” from memory alone.
However, fundus photography may not measure retinal thickness as precisely as OCT. It can suggest macular edema, especially when hard exudates appear near the macula, but OCT is typically better for confirming and quantifying swelling.
5. Fluorescein Angiography
Fluorescein angiography, often called FA, helps doctors see blood flow and leakage in the retina. A fluorescent dye is injected into a vein, usually in the arm. As the dye travels through retinal blood vessels, a special camera takes images. Leaking areas glow on the images, helping the doctor identify where fluid is coming from.
FA may be recommended when the doctor needs more detail about:
- Which blood vessels are leaking
- Areas of poor blood flow or blocked capillaries
- Abnormal new blood vessels
- The pattern of diabetic retinopathy
- Whether laser treatment may be useful
Some patients notice temporary yellowing of the skin or bright yellow urine after the test as the dye leaves the body. Mild nausea can occur. Serious allergic reactions are uncommon, but patients should tell the doctor about allergies, pregnancy, kidney disease, or past reactions to dye before the test.
6. OCT Angiography (OCT-A)
OCT angiography, or OCT-A, is a newer imaging method that can show blood flow in retinal vessels without dye injection. It uses repeated OCT scans to detect motion from blood cells moving through vessels. OCT-A can help doctors evaluate capillary dropout, abnormal blood flow, and changes in the macular circulation.
OCT-A does not fully replace fluorescein angiography in every situation because FA still shows leakage patterns clearly. But OCT-A can be useful when dye injection is not ideal or when the doctor wants additional detail about retinal blood flow. In short, OCT-A is like a high-tech traffic map for tiny retinal roads.
7. Slit-Lamp Exam and Retinal Examination
A slit lamp is a microscope with a bright light that allows the doctor to examine the front and back of the eye. With special lenses, the doctor can view the macula and retina in detail. This exam often happens during the same visit as dilation.
The slit-lamp exam may also reveal other eye conditions that can affect vision, such as cataracts, glaucoma-related changes, or inflammation. That matters because not every vision complaint in a person with diabetes is caused by DME. Sometimes the eye has more than one problem at once, because apparently eyes enjoy multitasking.
8. Amsler Grid Testing
An Amsler grid is a simple square grid used to check central vision distortion. The patient looks at a central dot and reports whether any lines appear wavy, missing, blurry, or distorted. This test is not enough to diagnose DME by itself, but it can help detect changes in central vision.
Some doctors may recommend using an Amsler grid at home, especially for people at risk of macular disease. If the grid suddenly looks different, it is a reason to contact an eye care professional promptly.
How Doctors Confirm a DME Diagnosis
A diagnosis of diabetic macular edema is usually based on a combination of findings, not one single clue. The doctor considers your diabetes history, symptoms, visual acuity, retinal exam, OCT results, and sometimes angiography findings.
The key diagnostic question is whether there is swelling or fluid in the macula caused by diabetic blood vessel leakage. OCT often provides the clearest measurement of retinal thickening and fluid location. FA may help confirm leakage and guide treatment planning. Fundus photos and clinical exam help document diabetic retinopathy severity.
The doctor may describe DME in several ways:
- Center-involved DME: swelling affects the central macula.
- Non-center-involved DME: swelling is near the macula but not directly involving the center.
- Mild, moderate, or severe DME: based on swelling, vision, and imaging findings.
- Clinically significant macular edema: an older but still recognized concept based on retinal thickening and hard exudates near the macula.
Why Early Diagnosis Matters
Early diagnosis gives patients more options. DME can often be treated with medications injected into the eye, laser therapy in selected cases, corticosteroid treatments, or a combination of approaches. The best treatment depends on the location of swelling, vision level, retinal findings, other eye conditions, and overall health.
Waiting until vision is badly affected can make recovery harder. The macula is delicate. Once retinal cells are damaged, treatment may improve swelling but not always restore perfect vision. That is why routine diabetic eye exams matter even when vision seems normal.
How Often Should People With Diabetes Be Checked?
People with diabetes should follow a regular eye exam schedule recommended by their healthcare team. Many adults with type 2 diabetes are advised to have a comprehensive dilated eye exam at diagnosis because diabetes may have been present for years before it was discovered. Adults with type 1 diabetes are commonly advised to begin screening within a few years after diagnosis, depending on age and clinical guidance. After that, many people need yearly exams, though the schedule may be adjusted based on whether retinopathy is present, how severe it is, pregnancy status, and overall diabetes control.
If diabetic retinopathy or DME is already present, exams may be needed more often. A retina specialist may monitor active DME every few weeks or months, especially during treatment. The follow-up schedule is not a punishment; it is surveillance. Your retina is not on trial, but it is definitely being watched.
What to Expect at a DME Testing Appointment
A typical appointment may include medical history questions, vision testing, eye pressure measurement, pupil dilation, retinal examination, OCT scans, and possibly retinal photography or fluorescein angiography. The visit may take longer than a standard glasses exam, especially if multiple imaging tests are done.
Bring a list of medications, recent A1C results if available, blood pressure history, and any previous eye records. Tell the doctor about vision changes, even if they seem small. “My reading vision gets weird at night” is useful information. So is “straight lines look bent” or “my left eye seems foggier than my right.” Your doctor is not expecting poetry, just clues.
Questions to Ask After Testing
After the exam, patients should feel comfortable asking direct questions. Useful questions include:
- Do I have diabetic macular edema?
- Is the swelling center-involved?
- How is my visual acuity today?
- What did the OCT show?
- Do I need fluorescein angiography or additional imaging?
- How severe is my diabetic retinopathy?
- Do I need treatment now or monitoring?
- How often should I return?
- What blood sugar, blood pressure, or cholesterol goals should I discuss with my primary doctor?
Good questions help turn a medical visit from a mysterious eye-light festival into an actual plan.
Conditions That Can Look Similar to DME
Diabetic macular edema is not the only cause of macular swelling or central vision changes. Doctors may consider other possibilities, including age-related macular degeneration, retinal vein occlusion, inflammatory eye disease, cystoid macular edema after surgery, medication-related swelling, vitreomacular traction, and other retinal disorders.
This is another reason imaging matters. Symptoms alone are not specific enough. Two people can both say, “My vision is blurry,” and one may need new glasses while the other needs urgent retina care. The eye chart does not tell the whole story; the retina scan often does.
Practical Experience: What Patients Often Notice During DME Testing
For many patients, the most memorable part of diabetic macular edema testing is not the technology. It is the anxiety before the visit. People worry that the doctor will find something serious, that the tests will hurt, or that they will be blamed for imperfect blood sugar control. That fear is understandable, but it should not keep anyone away from care. Eye doctors are there to find problems early and protect vision, not deliver a lecture with a side of guilt.
The first experience is usually easier than expected. The visual acuity test feels familiar. The dilation drops may sting for a few seconds, but the sensation passes quickly. Waiting for the pupils to widen can feel oddly dramatic, as if the eyes are preparing for a tiny movie premiere. Once dilated, near vision becomes blurry, phone screens look too bright, and sunlight may feel rude. Sunglasses become the hero of the day.
The OCT scan is often the test that surprises people most. It looks advanced, but it is simple from the patient’s side. You sit still, rest your chin, look at a target, and let the machine do the work. There is no contact with the eye. No puff of air. No needle. The scan produces detailed images that many doctors will show on a screen. Patients often understand their condition better when they can actually see the swollen retinal layers. A picture of fluid in the macula is more persuasive than a vague statement like “things are puffy back there.”
Fluorescein angiography can feel more intimidating because it involves dye injection. The needle is usually the same kind used for a routine blood draw or IV placement. After the dye enters the bloodstream, the imaging happens quickly. The camera may flash several times, and the room may feel busy for a few minutes. Some people feel slightly nauseated, but it usually passes. The bright yellow urine afterward can be surprising if nobody warns you. It is normal and temporary, though admittedly it does make the bathroom experience feel like a science experiment.
One practical tip is to avoid scheduling important reading, driving, or screen-heavy work immediately after a dilated exam. Even if you feel fine, your eyes may not be ready to negotiate spreadsheets, traffic glare, or tiny text messages. Another tip is to bring previous eye records if you are seeing a new doctor. Retinal changes over time can be just as important as a single image.
The emotional experience matters too. A DME diagnosis can feel scary, especially when vision is involved. But diagnosis is also the doorway to treatment. Many people with diabetic macular edema maintain useful vision for years with timely care, regular monitoring, and better control of diabetes-related risk factors. The goal is not perfection. The goal is action: show up for exams, understand the results, follow the treatment plan, and keep the rest of the healthcare team involved.
Conclusion
Diabetic macular edema tests and diagnosis are all about seeing what the naked eye and everyday vision cannot reliably reveal. A comprehensive dilated eye exam gives the doctor a direct view of the retina. OCT measures swelling and fluid with remarkable detail. Fundus photography documents retinal changes. Fluorescein angiography shows leakage and blood flow patterns. OCT angiography can add more information without dye in selected cases.
The most important message is simple: do not wait for major vision loss before getting checked. DME can develop quietly, and early diagnosis gives treatment the best chance to protect central vision. If you have diabetes, routine eye exams are not just another item on the health checklist. They are vision insurance, minus the confusing fine print.
Note: This article is for educational purposes only and should not replace medical advice from an ophthalmologist, optometrist, retina specialist, or diabetes care professional. Anyone with diabetes and new vision changes should seek prompt eye care.